
During 2022, NHS Gloucestershire’s children and young people’s mental health services launched its digital support finder. Beth Gibbons explains how her team at NHS Gloucestershire created On Your Mind Glos to give young people more control of their care.
With the support of tech specialists, Made Tech and Mace and Menter, we have created a team of designers and technologists along with our NHS staff to research and build this new mental health tool. The work was commissioned rather than built in house because of the specialist skills and capabilities needed around service design and agile service delivery. The team worked with clinicians, frontline workers, children, young people and the local community to research user needs. We found that interaction with these specific groups was crucial to help us create a tool that truly worked for those it needed to. Mental health support practitioners, GPs, school nurses and mental health leads in schools were also included in the research to help us understand the specific problems that needed fixing.
A single source for local mental health support information
The online support finder on the dedicated website guides users through a series of questions to understand how they’re feeling and what support they might need. They’re then signposted to the most relevant service for their needs and given useful information about mental health.
The results are available to young people, their parents and carers via the website and SMS. Providing SMS access was an important element of the service as it needed to be accessible and secure for any child or young person to use, regardless of their access to a computer. Just three months after the initial launch, a round of user research revealed that young people like using the service, with more than 2,500 visiting the site.
Today, the support finder is an easier solution for young people to understand, find and access over 100 mental health support services and gives them more choice and control of their care. For health practitioners it provides accurate advice and helps them signpost to services.
It has since been launched in schools alongside a programme of mental health awareness and has reached around 10,000 young people. While it was developed for young people, it’s expected that professionals, parents and carers will use it too.
‘Dementia-branded’ products are improving people’s lives, but can off-the-shelf alternatives do the same and save people money? My research suggests that they can. The ‘cost of living crisis’ and the lasting legacy of the COVID-19 pandemic have further exposed the countries’ health and social inequalities. Often absent from debate is the digital divide, which considers the gap in society between those who have access to digital technologies and those who do not. I began to examine the digital divide in relation to people living with dementia in early 2019, for my PhD in Digital Health. Motivated by the belief that everyone deserves equal opportunity to benefit from technology, and a personal connection to dementia, I set about exploring the use of Global Positioning System (GPS) technology by people living dementia and their families. The technology is widely used in dementia care to support independence and help keep a person living at home in the community. As this technology has become more widespread, an industry has formed around marketing ‘dementia-branded’ GPS products, that can retail from upwards of £100.

People living with dementia and carers told me that the price of these products was excessive and, for many, was beyond their reach. This resulted in them being excluded from gaining the benefits that GPS and other devices offer.
Off-the-shelf alternatives
Off-the-shelf products are readily available, without a specific use attached, and can be purchased online on marketplaces such as Amazon and eBay for around £10-£30. Through a series of focus groups and interviews, I presented a low-cost alternative through ‘off-the-shelf’ GPS devices. People living with dementia and their families chose a device that was then provided for them to try out. They were asked to use these devices alongside their daily lives, as I examined adoption, acceptance, and in one case abandonment, of this technology.
Awareness and training
My research demonstrated that off-the-shelf technology presents a viable, inclusive alternative, to ‘dementia-branded’ products. However, access is not the only barrier, but also awareness and education. Participants reported that more needs to be done to raise the profile of ‘off-the-shelf’ alternatives to assistive technologies, as they have a role to play in reducing disparity in health and social care and increase access to potentially vital technology.
In terms of education, to assist participants in my study I created a website and online training tool. Educational resources were co-produced with older adults and people living with the condition, and available in various formats including instructional videos to teach participants certain features, and a step-by-step user guide. In the future, to raise awareness of alternative options in technology, my plans are to repurpose this website to provide information on how to purchase low-cost off-the-shelf assistive technology and continue to provide advice and online training.
Largely driven by the pandemic, the social care sector in Wales has seen a fast-paced switch from face-to-face to digital forms of workforce training and development. To better understand the benefits and challenges of digital learning, Social Care Wales commissioned SCIE to undertake an evidence review and activities with staff to hear about their experiences. Amongst the issues discussed, digital literacy was one of the most common. Digital learning requires learners to operate devices and navigate through digital resources such as websites and learning applications. For staff that struggle with this, it can be a major barrier to digital learning. When we spoke to social care staff, they discussed two related issues:

Digital skills
The first issue is about digital skills themselves. The social care workforce in Wales is very diverse and includes people from different age groups and with all sorts of professional experience and skills. This means that, as in many sectors, some of the workforce requires specific training and support to develop digital skills to access digital learning resources.
Digital confidence
The second issue relates to how comfortable and confident staff members feel when using digital learning resources. While the two are related, we found that developing digital skills does not necessarily equate to developing digital confidence. Often, individuals use digital devices for everyday tasks such as shopping, using maps, and web searches, but still don’t feel confident when accessing digital learning. For some people, this is related to how the digital learning platforms they have tried using have been developed. Some platforms focus more on recording progress and performance than on how the staff feel and experience the resource. As a result, staff can be unsure about key tasks such as logging in and navigating through the resource. A negative experience can affect how the individual feels about the learning process and be as much of a barrier to digital learning as a lack of digital skills.
Understanding digital literacy as a twofold issue can help to create joined-up solutions to support the uptake and experience of digital learning. While basic digital skills can be supported with training and upskilling approaches, the development of confidence needs a tailored approach with, for example, coaching sessions to support staff to transfer digital skills they already have, and, most importantly, providing user-friendly resources and devices that staff find intuitive.
You can find out more about the impacts, benefits, and challenges of digital learning for the social care workforce, as well as our recommendations to guide future approaches to digital learning in Wales in our report below.
In 2009 I started my Social Work journey in North Yorkshire supporting adults to remain at home for as long as possible. I met people who had lived a long life without drawing on statutory care and support and were coming to terms with a loss of independence and the need to consider care for the first time. I met families who had cared for their loved ones for many years and were struggling with the emotional and physical requirements of the role and needed support. I also met young people who due to an unexpected situation in their life were now calling on care. I later moved to work with people with learning disabilities, Autistic people and people who had been in contact with mental health services.

I’ve supported people to move from residential care into their own home, which came with significant challenges from the care system and clinicians around them, where historical incidents were recorded and left unchallenged for decades and underpinned a restrictive approach to their care. One experience that continues to resonate with me, is where a person who had allegedly set fire to a bin as a teenager, 10 years prior, was moved from his family home to residential care and remained there over 10 years later with a folder detailing ‘risks’ if he were unsupervised.
The person was also repeatedly recorded as ‘lacking capacity’. I presented him with pictorial information about moving home, referred him for an advocate and eventually he began to talk to me about his life and what was important to him. He needed a little support to understand budgeting, but was already working in his local community, we worked together to move him to his own home and I saw his confidence grow. I’ll never forget the day of the move, carrying his treasured fish tank and fish in the car to his new home, but seeing him set his bedroom up, how he finally wanted it. What I have learned is to use my leadership skills as a Social Worker, to spend time getting to know people, the way they want to be communicated with, and help people to speak up using advocacy support and continue to pursue less restrictive care when everyone felt it too risky.
This is the key to preparing for Liberty Protection Safeguards (LPS), recognising what restrictions look like, recognising that even when people are not demonstrating they are ‘unhappy’ with their care arrangements, they still may be deprived of their liberty and have a Right to liberty.
A flourishing life?
Liberty is not an absolute Right, it can be curtailed but must follow a process set out in law (for example, using Deprivation of Liberty Safeguards). But even when a person requires a level of care that amounts to a Deprivation of Liberty, are we doing enough to ensure that restrictions are not just accepted as the status quo? Are we focusing on a person’s need to live a flourishing life?
During the height of the current Pandemic, we all experienced a restriction on our liberty to prevent the spread of an infectious disease. However, once restrictions were lifted, disabled people continued to experience restrictions in their everyday life, including continued restrictions on family visits, leaving their homes and continued requirements to test regularly. Even when blanket restrictions are/were unlawful under the Mental Capacity Act, we continue/d to see evidence of blanket restrictions being applied, particularly around family visits. Disabled people continue to be far more restricted in their everyday life compared to the general public.
Being proportionate
Every practitioner I know has made a decision at some point to provide care to a person who is unable to make the decision themselves (under the Mental Capacity Act). However what is much rarer is naming arrangements when they become a ‘Deprivation of Liberty’ and identifying why those arrangements are both necessary and proportionate.
The State, the local authority, is the servant of those in need of its support and assistance, not their master.Lord Justice Munby A Local Authority v A (A Child)& Anor [2010] EWHC 978
If you are a practitioner and have increased the level of observation a person is subject to, introducing people to their life to provide care, reduced a person’s choices, you need to consider how you are implementing the care in a way that promotes Liberty rather than just restrict. Preparing for LPS involves becoming familiar with Deprivation of Liberty Safeguards now, recognise when you make decisions that impact on a person’s liberty, and record it. Being a Rights based practitioner means challenging the status quo, think outside the box and promote social justice .You don’t have to be an Approved Mental Health Professional (AMHP – Mental Health Act) or Best Interests Assessor (BIA – Deprivation of Liberty Safeguards) to be Rights based, you just have work get to know the people you work with and the impact of your role, and decision making, in their lives.
LPS does not yet have a new implementation date, but there is plenty to do to prepare in the meantime. People don’t want to be over processed in order to access their Safeguards under LPS, we should be looking at how we can incorporate the information into everyday practice, for example as part of Care Act processes. As soon as you determine a person is unable to make a decision about their care and where they live, start to think about how to promote and maintain Liberty throughout practice, keep working to reduce unnecessary restrictions, always ask: Is this Necessary? Is this proportionate?
It’s been a long time since I’d attended an in-person event due to Covid and working remotely. But, during Co-production Week 2022, we held a panel event and I had the opportunity to be there. I had best view of it, sitting at the back on my laptop taking notes and taking it all in. Co-production is about working in equal partnership with people using services, carers, families and citizens. In that room in early July, there was a diverse presence, from Social Care Leads, Heads of Services, Project Managers, Population Health Programme Manager, Quality and Compliance Manager, Lived Experience Lead, Head of Community Participation; and others from various charities and health and social care settings.

- SCIE report: Developing our understanding of the difference co-production makes in social care
- Co-production Week
It was interesting to hear questions on sustainability of co-production methods and building on the support of senior leadership, especially when roles change or someone leaves their job. How does one prevent coproduction from slipping through when there’s a lot to juggle? How do we engage the people we want to work with and gain their trust, without ticking checkboxes whilst ensuring that funding is justified through demonstrating impactful evidence?
Then following on from what Andy, Director of Involvement at Revolving Doors charity, said, find out your workplace priorities and challenges, what needs to be addressed and offer co-production as a solution; rather than merely presenting co-production as a separate approach to existing ways of working.
Being the designated notetaker during the event meant I could swap the screen to Twitter. I saw people from the event posting pictures of the presentation and quoting the panellists, which was so encouraging to see. The room was buzzing with conversations, and I can’t wait to attend further face-to-face SCIE events soon.
Panellists on the day
- Andy Williams – Director of Involvement, Revolving Doors charity
- Deborah Rozansky – Director of Policy, Research and Information SCIE
- Fiona Flowers – Head of Practice Development SCIE
- Kathryn Smith – Chief Executive of SCIE
- Kevin Minier – Co-production Board Member SCIE.
Face-to-face events coming soon
A panel event giving insights into the local government care reforms. If you would like to be notified about these events, please let us know by emailing: info@scie.org.uk.
Beve Smith is an ex-midwife, has lived experience as a carer and is a member of the Kirklees Co-production Board. Dulcie Leach is retired from educational services, has lived experience as a carer and is also a member of the Kirklees Co-production Board. Alex Chaplin is a Policy Officer at Kirklees Council. Tamsin Macdonald is manager of Kirklees’ Local Area Coordination Programme. Tamsin: 2020 was an exciting time because it was when the Council published our Five year Vision for Adult Social Care. Within the vision it says: “Our vision is about people as active and equal partners in how we work together to co-produce, co-design, co-deliver and co-evaluate care services in Kirklees”

With some support from The Social Care Institute for Excellence (SCIE) we coproduced a plan and decided to try and test and learn through taking a co-productive approach to two projects – Developing an integrated contact centre service for health and care and reviewing our Direct Payments policy. It was through this work Alex and I met Beve and Dulcie and together with many others, we also created a new Coproduction Board.
Dulcie: There was a wide breadth of people when we met at the beginning. We didn’t know each other and some of us were quite hesitant. Through some long conversations, we started to realise that we all had shared stories and experiences. We were wondering if we would be listened to and truly heard. Some people said “we’ve been here before and it didn’t work out”. We had lots of conversations to unpick this at the beginning, questioning if we would ever see the fruits of our labour.
Tamsin: As council officers, some of us also felt hesitant. We didn’t know what the outcome was going to be and we couldn’t predict the timelines. That can be quite a scary space for people to step in to, I think.
Alex: One thing I’m really proud of is that we have come past that now and are starting to see our coproduction journey move into the next phase with the review of the Direct Payments policy. We now have all the documents signed off and we are beginning the work of embedding this new improved version with training and things like that.
Tamsin: We’re all really hopeful that ultimately this will lead to more people across Kirklees receiving a Direct Payment that helps them achieve their vision of a good life, feel more independent and in control.
Dulcie: Some people think that when people get together, they are going to ask for heaven and earth or make unreasonable demands. In the coproduced work that we’ve been involved in, we’ve found that all people really want in terms of their care and support are the things that anyone would want to live a good and normal life. To be a part of community, have friendships and good relationships.
Beve: We know we’re getting it right when it feels like a meeting of equals. We’ve all been kept in the loop all the way through and feel that we have truly participated in the process. We talk about power sharing a lot and this is what it feels like. Moving from a sense that things are being done to us, to a place where we are all moving together in the same direction. We’re starting a movement. It feels like being a part of the change we want to see.
Dulcie: We have lots of things we can be proud of. We might not always agree with each other, but we appreciate what each other’s strengths are and have respect for each other.
Tamsin: It’s about getting there in a steady way where we all feel like we are a part of something. Everyone has something to offer, it is just a matter of working out ways that people can contribute. That’s why it’s so important to get to know each other, learn about each other, and share our gifts with each other.
Beve: It’s not actually as radical as it seems. It is radical in terms of what can be achieved but it’s not as hard as we thought it would be.
Alex: It’s definitely worthwhile doing. It just takes a leap of faith, quite a bit of confidence and most importantly… a lot of time! But what you come out with at the end is really invaluable.
Valerie Wood is a full time unpaid carer who retired from the NHS to be a care partner for her husband, who has Motor Neurone Disease. Bryony Shannon is the Strategic Lead for Practice Development in Adults, Health and Wellbeing at Doncaster Council.
Getting started
Valerie: It just happened. It wasn’t like I knew what I was doing! I’ve been campaigning for years, and I started getting interested in the #SocialCareFuture movement on Twitter and came across Bryony’s blog about how language in health and social care can create barriers, and this really got me thinking about how I could influence change in a more ‘hands on’ way. I was already involved in the Carers Action Group in Doncaster, then Bryony asked me if I’d like to join some workshops looking at people’s experiences of access to care and support. Bryony: When I first got this job, I didn’t really know how to get started with embedding co-production. But our approach has evolved organically through lots of connections and conversations, and it’s become really clear to me that – as with most things in social care – co-production is all about relationships.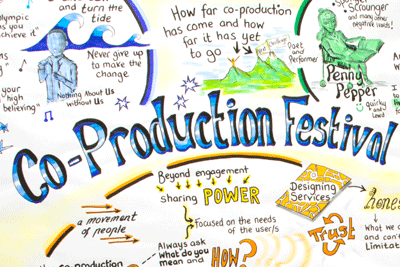
Wait a minute!
Valerie: I come across the word co-production in an awful lot of reading material. You trust when people mention co-production that it is co-production, but then the more I found out about it, the more I learnt, I realised that the word co-production was being compromised. And then you think, wait a minute! If you’re saying you do co-production, then do it. If you’re not doing it, fine. But don’t tell me you’re doing it when you’re not.
Bryony: I remember sharing the ladder of co-production with Valerie. That’s when we realised that lots of ‘co-production’ she’d been involved in was actually consultation or engagement. Looking at the ladder of co-production together really helped.
Valerie: I also find Think Local Act Personal’s (TLAP) Ten top tips for co-production useful. I use that regularly. Often professionals tell us they want to co-produce something, then put the pressure on us to get through things quickly. If you want us to be part of things, you have to give us time.
Bryony: Co-production is about creating something together. Co. Production. And if you’re going to do co-production properly, you’ve got to acknowledge it takes time. But it’s time well spent, isn’t it? Because you’re getting things right and doing them in the right way.
Valerie: Our work on the principles met all those top tips for co-production
Co-producing our practice principles
Bryony: We’d adopted the #SocialCareFuture vision and signed up to TLAP’s Making it Real framework, but I was also keen to co-produce some local principles to underpin our practice. We drew together a small group of people with lived experience and people working in Adults, Health and Wellbeing to talk about what those principles could be.
Valerie: We started with an idea that blossomed. Bryony ensured everybody had an equal status and an equal say. I never ever felt that anybody was more important in that group. We decided how we were going to work together and how we would make a difference. Bryony supplied the background information – you can’t go into any of these workshops and be a true partner if you haven’t got the background information supplied to you, then it’s up to you whether you read it or not.
I did get confused sometimes though. The professionals were chatting away like nobody’s business and I had to keep asking if they could explain this and that. I think you do need to consider how much information is needed and not make assumptions. I didn’t know about TLAP or the Be Human Movement then. But it was good. I liked it.
I think personalised care keeps getting missed out, I really do. It’s still very much service centred, not person centred. I feel like we’re very good on paper now, we’ve got a good framework. I really do believe in it. But now it’s about making sure it gets translated into practice. That’s the really important bit.
The next step for me is for the co-production to work in practice and be meaningful for people to have the social care future they hope for, and for the framework we all co-produced.to be fully supported by an excellent implementation plan.
This is the 7th year of the SCIE Co-Production Annual Festival. I would like to draw your attention to some significant connections with Co-Production and the Care Act 2014 and its Well-Being Principle and how these have directly changed the lives of many people with lived experience for the better. It is not surprising that one of the most comprehensive pieces of disability legislation in the history of social and health care, the Care Act 2014, should be the first piece of legislation to include co-production. Co-production began to have an impact towards the end of the first decade of the new millennium. People with lived experience realised that co-production could have a beneficial effect when working together with different health and social care authorities. I personally did some work on this when I was working for the Department of Health (DH), as it was called then between 2008-2010. I was the DH Specialist on ULO’s (User Led Organisation) and we tried encouraging ULO’s in different regions to work together in partnership on an equal basis with their authorities to co-produce.

This is what the Act says about the effect the individual can have on the co-production process: “when an individual influences the support and services received, or when groups of people get together to influence the way services are designed, commissioned and delivered”. This statement encapsulates everything that the disability movement have been attempting to do for decades. In the beginning when Independent Living was established in the early 1980s, one of its main principles was that “any decision made about a disabled person’s life should directly include them in the process”. This is exactly where the term “nothing about us without us” came into being. It is also where the whole concept of “person centred approach and thinking” came about.
Co-production features in several parts of the guidance in the Care Act and in particular the section on Prevention. It says “in developing and delivering preventative approaches to care and support, local authorities should ensure that individuals are not seen as passive recipients of support services but are able to design care and support, based around the achievements of their goals. Local authorities should actively promote participation in providing interventions that are co-produced with individuals, families, friends and the community.”
I think another important aspect which also appears in the Care Act is the connection with the well-being principle. I firmly believe that co-production has had such a positive and powerful outcome in terms of what can happen when its dynamic is used in designing services and the impact this can have for the individual. I have witnessed so many times how this positive outcome can have beneficial effects on the individuals involved. It can transform the quality of life, health and well-being of the people who are engaged in this process. Co-production can have a definite effect on the principle of well-being. We can experience and measure this by seeing the impact it has on individuals working together in partnership on an equal basis with different authorities. What can be better than this? I have also seen how this can improve the mental well-being of people who might experience mental health issues. This can be further developed and supported with peer support with people who have been through similar states of being.
In conclusion, one can see how these two essential principles of the Care Act, co-production and the well-being principle, can directly enhance an individual’s experience when engaged in designing services based on their own expertise and insight into their conditions along with other like-minded people.
In April and May 2022, SCIE facilitated four online sessions with people with lived experience and people who work in services to consider the impact of co-production. We wanted to learn about the difference that co-production makes to people’s lives. This blog briefly outlines what people said about the overall impact of co-production, and forms part of a longer briefing which will be launched during National Co-production Week 2022.

“Co-production doesn’t feel tokenistic anymore which is a huge change. We aren’t just stoking the engine; we are driving the train.”
Delegate.
Although it can sometimes be difficult to pinpoint the difference that co-production makes to services, participants mentioned a range of ways in which it has impacted on the health and social care landscape.
Co-production has helped to change the mindsets of people involved in health and social care. Some barriers have broken down and people with lived experience are being recognised as experts. It has helped to develop a richness in knowledge, through sharing good practice and communicating with a wide range of people. Co-production keeps things relevant in a rapidly changing world and increases credibility.
The relationship building element of co-production has helped members of the community feel valued and ensured that professionals attend key meetings. It has also played a significant role in promoting the idea that regulatory bodies and guidance should involve service users from the start.
One participant mentioned that guidelines about bedwetting she was involved in developing are still being talked about and used many years later, which has made a huge difference for children, parents and families throughout the country.
Participants also mentioned that co-production has provided opportunities for service users to work with professionals in interviewing students for university courses, and equipped people with lived experience with the skills and knowledge to find employment.
Although effective co-production can require considerable resources at the beginning, it becomes cost effective in the long run, once it is fully set up. Co-production can provide solutions to problems that you didn’t even know were there in the first place.
If the impact of co-production is to have meaning and power, it’s important not to give up, so we must remain persistent.
“The more we do good co-production, the more others will follow. It encourages further co-production.”
Delegate,
Thinking back to the implementation of DoLS – Deprivation of Liberty Safeguards – I recall the anxiety generated across the country in 2009 as April approached and the embryonic DoLS services awaited the barrage of requests for standard authorisations. Would we be able to cope? How many staff would we need to manage the demand? The 1 April came and there was no barrage; hardly even a ripple Just as the Millennium Bug turned out to be a myth, so (on a much less global level, obviously!) did DoLS not produce the Armageddon that local authorities were fearing. Some local authorities only had a handful of cases during the first year – imagine that!

Planning for LPS
Just like the excitement generated in ‘96 when the country was gripped by hope that England bring home the Euros Cup, I am cautiously optimistic that LPS will bring protection of liberty into the care and support functions of the sector.
When preparing for LPS, the government has stated that much of the documentation is already there and DoLS is just duplicating work. I believe that has not always been the case, but there is an opportunity to plan for the new scheme and minimise the additional work required, by ensuring that the core Mental Capacity Act (MCA) principles are followed in the initial assessment and care planning processes.
If robust capacity assessments and well-documented best interest decisions are on file, this will significantly reduce the additional burden when making authorisations for LPS. And it’s doing no more than following the requirements of the legislation since 2007.
We don’t yet know exactly when LPS will be implemented, but this is work that can be done now to ensure high quality and legally defensible practice for now and for the forthcoming changes.
In 2018, when we penned ’Asset Based Commissioning – Better Outcomes and Better Value’, we were convinced that individuals could get closer to experiencing the lives they wished, in the sort of community they wished. A key factor to realising this is that individuals and communities understand the assets they control and are willing and able to use these effectively.

No way did we foresee the vast release of additional individual and community assets prompted by Covid 19. Progress that we thought might take ten years, happened in weeks. Covid has spurred individual and community self-help and the flexing of services to support what people were already doing to help themselves. No stats yet on the volume of self-help and volunteering, but in time we will understand this and the profile of ‘covid volunteers’; what they did, why, how many first-time volunteers etc. Where organisations were a galvanising force, we will understand the types and sizes, which pre-existed covid, which were quickly established, what worked and why.
The Public Service Transformation Academy has been focused on teaching the potential paradigm shifts in commissioning through the Cabinet Office Commissioning Academy
Volunteering may reduce during Waves 2 and 3 and beyond, due to perceived reduced need, state intervention, volunteers coming off furlough, and individuals being unable to sustain crisis level effort. This is all understandable but hopefully, levels of self-help and volunteering will still exceed pre-covid days.
The attitudes and actions of commissioners will have a significant impact. Some will seek to:
- Build on the progress in self-help and volunteering made over the last eighteen months, supporting individuals and fledgling community organisations, in the process boosting asset based commissioning
- Whilst others will try to reassert control and consistency, through imposing standard specifications, regulation, reporting requirements
Amongst the horrors of Covid-19 there been positives, more than just a vast increase in volunteering; we think there has been a shift in who was involved, who exercised leadership, the relationship between citizens, volunteers, and the state, how needs emerged and were prioritised.
Covid dividend
Handled well, a paradigm shift in self-care and volunteering will be a significant ‘Covid dividend’. Handled badly and what could have been a paradigm shift will be little more than a paradigm skid or swerve.
We want to understand what commissioners are doing as the UK progressively opens- up. Tell us what you are seeing; actions to support and develop or a focus on reasserting control and consistency?
And if you’d like to participate in the Public Service Transformation Academy’s open learning community, join us on 23 June for the days after: are we learning? Are we building back better?
When SCIE started its first Co-Production Festival in 2016, it was a revolutionary moment in its history. The success of the festival was outstanding. As part of the Steering Group which was behind the planning of this event it was very satisfying and illuminating to witness its outcome for all of us involved. It remains my standout moment since I became involved with SCIE. I think its success was due to being a combination of both entertainment which included comedy, poetry and music performed by disabled artists, and serious reflection through interactive workshops and lectures. Another important aspect was the combination of attendees which was a mixture of health and social care professionals, and people with lived experience. This was a dynamic which was central in getting the important message of co-production across to its participants – especially the professionals.
The important point about the festival was to discuss how co-production can transform and inspire positive change.
When I started my own independent living scheme over three decades ago, the reason why I did this was because I felt very strongly that social care and health professionals should not be making decisions about my life, but I should. I was the expert about my life and not them! I think social care would be much weaker without the diverse voices and actions of many people who have expertise, and the experience of using the services. When people with lived experience are involved directly, you can guarantee that the social care services will be far better off than without them.
Over the last 20 years, SCIE has been at the forefront of developing co-production by seriously engaging people with lived experience, which is what attracted me to the organisation. In that time, SCIE has achieved some very important pieces of research and contributed to significant social change, so it has a worthy place in the improvement of society for people with diverse needs. It is vital that people like me are intrinsically engaged in all of its work to implement positive changes for the better.
The 20th year of SCIE’s existence also marks the sixth year of our Co-production Festival, and it is as popular as ever. We had to move the Festival online for the last couple of years, as a result of the COVID-19 pandemic, but this did not diminish the interest in it or its success. It was a different kind of dynamic, but showed the continued importance of co-production which grows more and more each year. It is as inspiring as ever to see health and social care professionals, and people with lived experience come together to celebrate the benefits of co-production in developing better public services.